
High-Grade Mucoepidermoid Carcinoma of the Parotid with Facial Nerve and Skin Involvement: Radical Parotidectomy, Radical Neck Dissection and PMMC Flap Reconstruction
Composite parotid resection with single-stage PMMC reconstruction. Intended audience: ENT residents, head and neck and plastic surgeons.
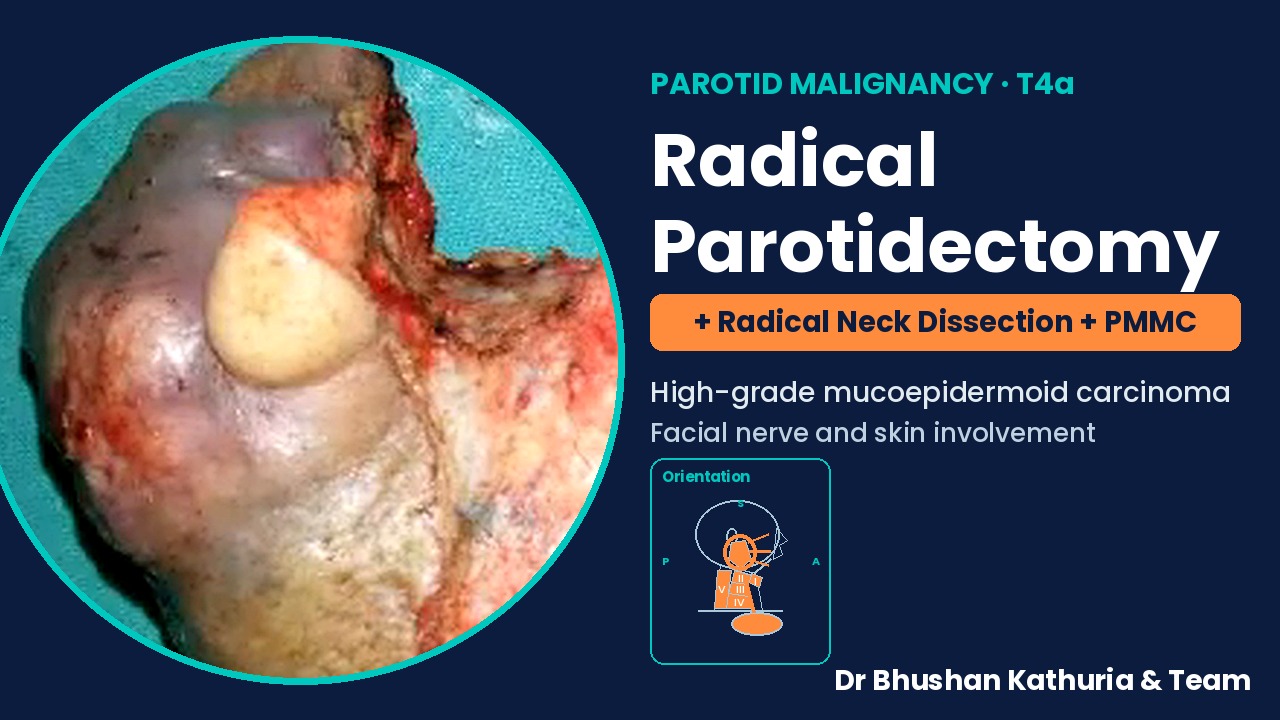
- Diagnosis
- High-grade mucoepidermoid carcinoma, parotid (T4a)
- Procedure
- Radical parotidectomy with skin and facial nerve
- Neck
- Radical neck dissection, levels I–V
- Reconstruction
- Pectoralis major myocutaneous flap
- Adjuvant
- Radiotherapy
- Video
- 3 min · step-by-step
Operative video with step captions and geometric orientation markings. Summary video.
Abstract
We present a T4a high-grade mucoepidermoid carcinoma of the right parotid with skin infiltration, a discharging sinus and established facial nerve palsy, with deep-lobe extension and cervical nodal disease. Management comprised radical parotidectomy en bloc with the overlying skin and facial nerve, radical neck dissection (levels I–V) and single-stage reconstruction with a pectoralis major myocutaneous (PMMC) flap, followed by adjuvant radiotherapy. Operative steps, a labelled post-dissection neck anatomy and geometric orientation are presented with the operative video.
Keywords: mucoepidermoid carcinoma; parotid cancer; radical parotidectomy; facial nerve sacrifice; radical neck dissection; pectoralis major myocutaneous flap
Introduction
Mucoepidermoid carcinoma is the most common malignant salivary gland tumour. High-grade tumours behave aggressively, with a substantial risk of nodal metastasis. Pre-operative facial nerve palsy in a parotid mass strongly suggests malignancy with perineural or direct nerve invasion [1].
Case presentation
A middle-aged man presented with a right parotid swelling with skin infiltration, a discharging sinus and complete ipsilateral facial palsy. Fine-needle aspiration cytology showed high-grade mucoepidermoid carcinoma. MRI demonstrated deep parotid extension and ipsilateral cervical lymphadenopathy. The mass measured about 6.5 × 7.75 cm (T4a).
Written informed consent for surgery and for de-identified educational use of images was obtained.
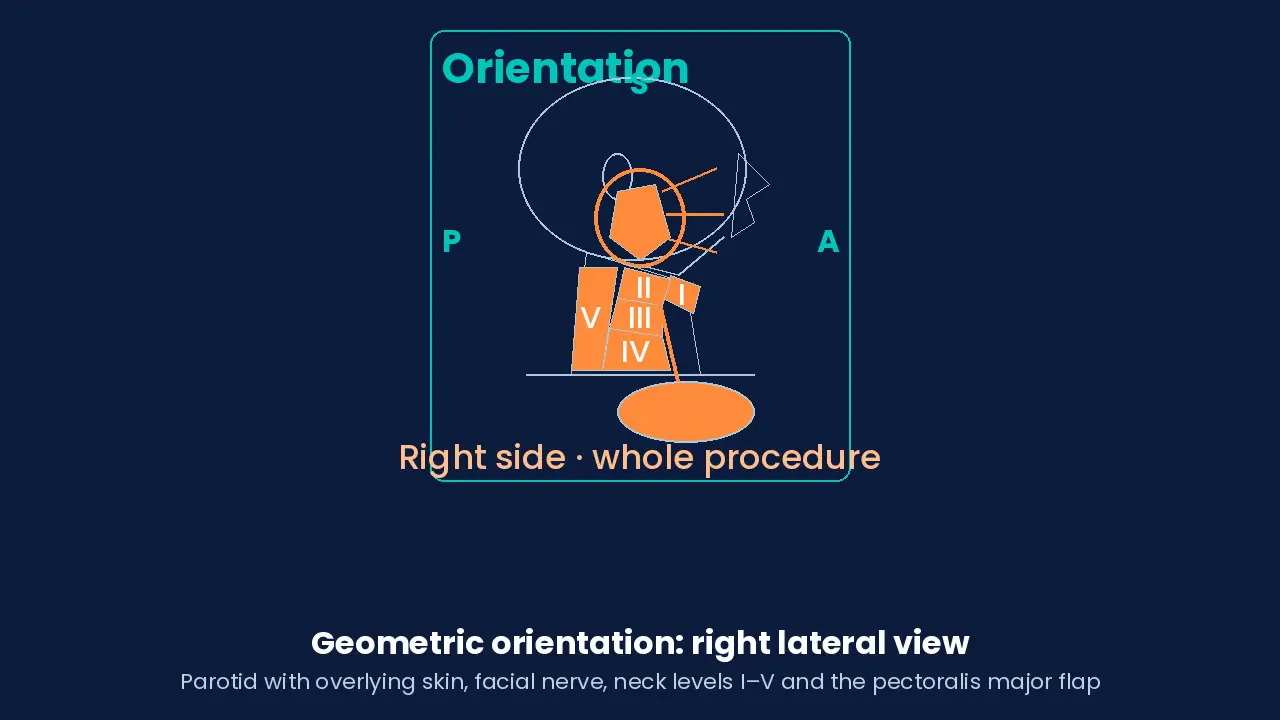
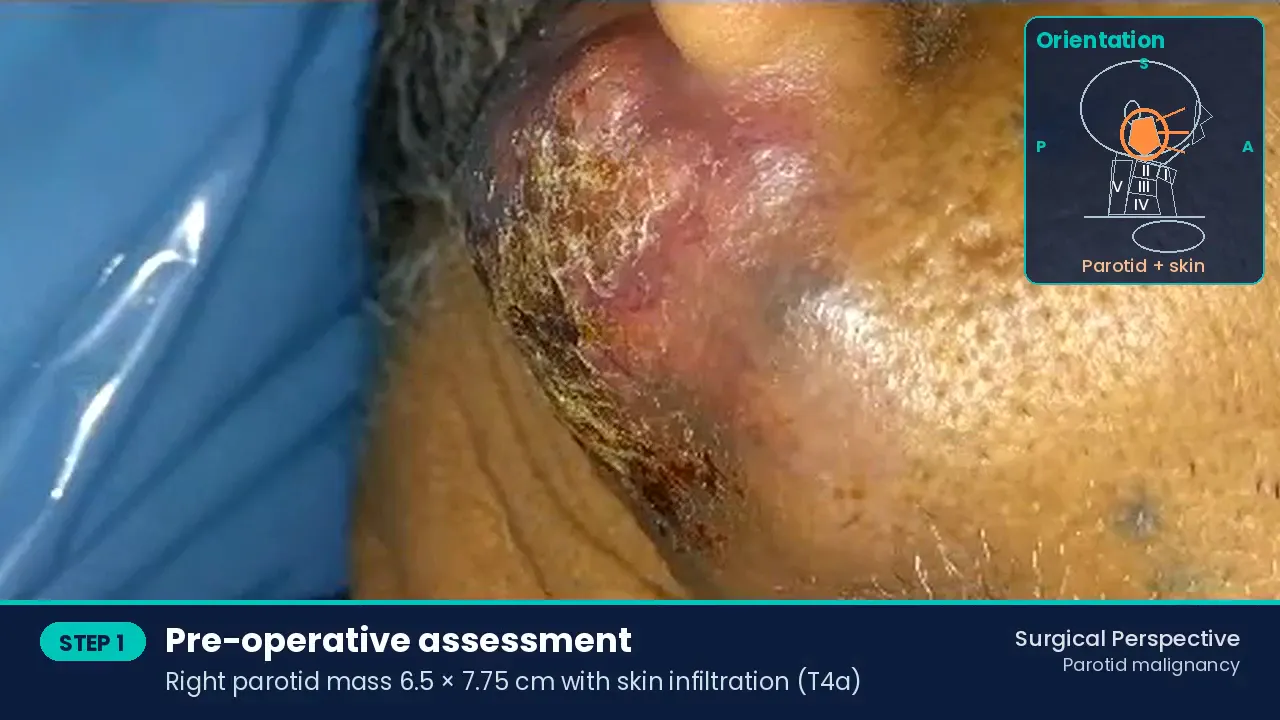
Surgical technique
Skin-margin marking
Elliptical excision with a safe skin margin, including the lower part of the ear lobule.
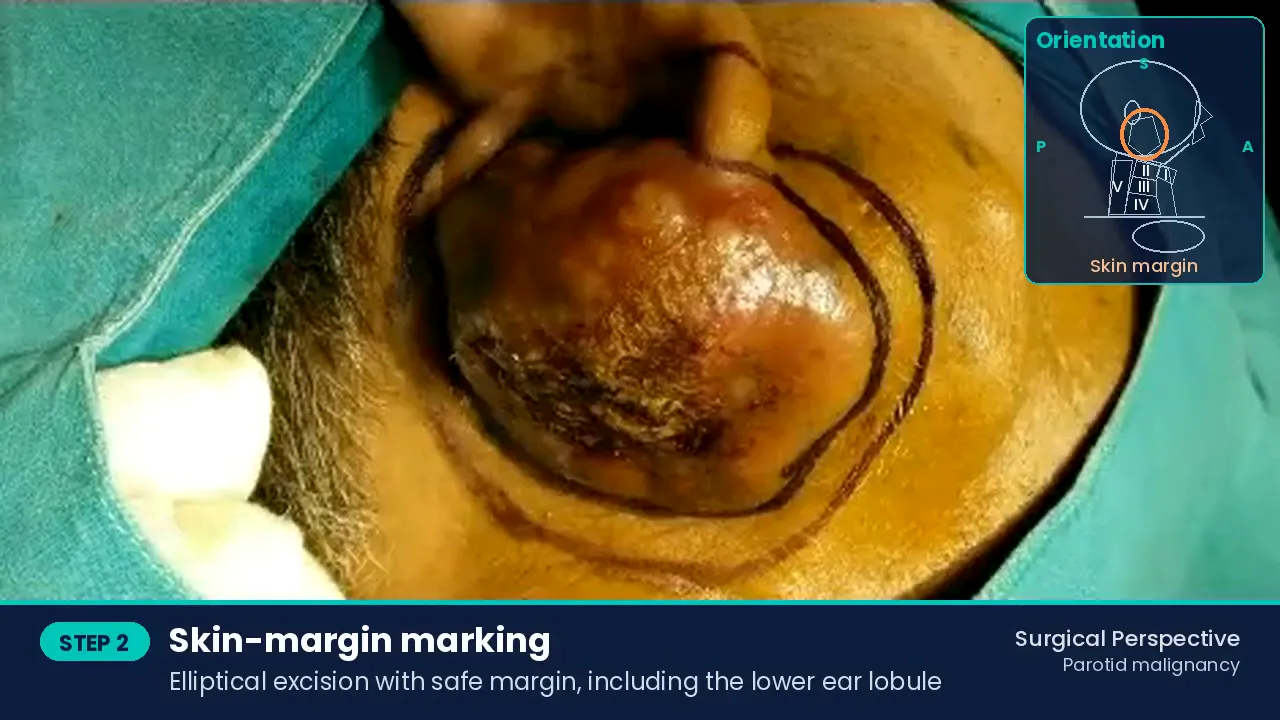
Skin-margin marking Radical parotidectomy, en bloc
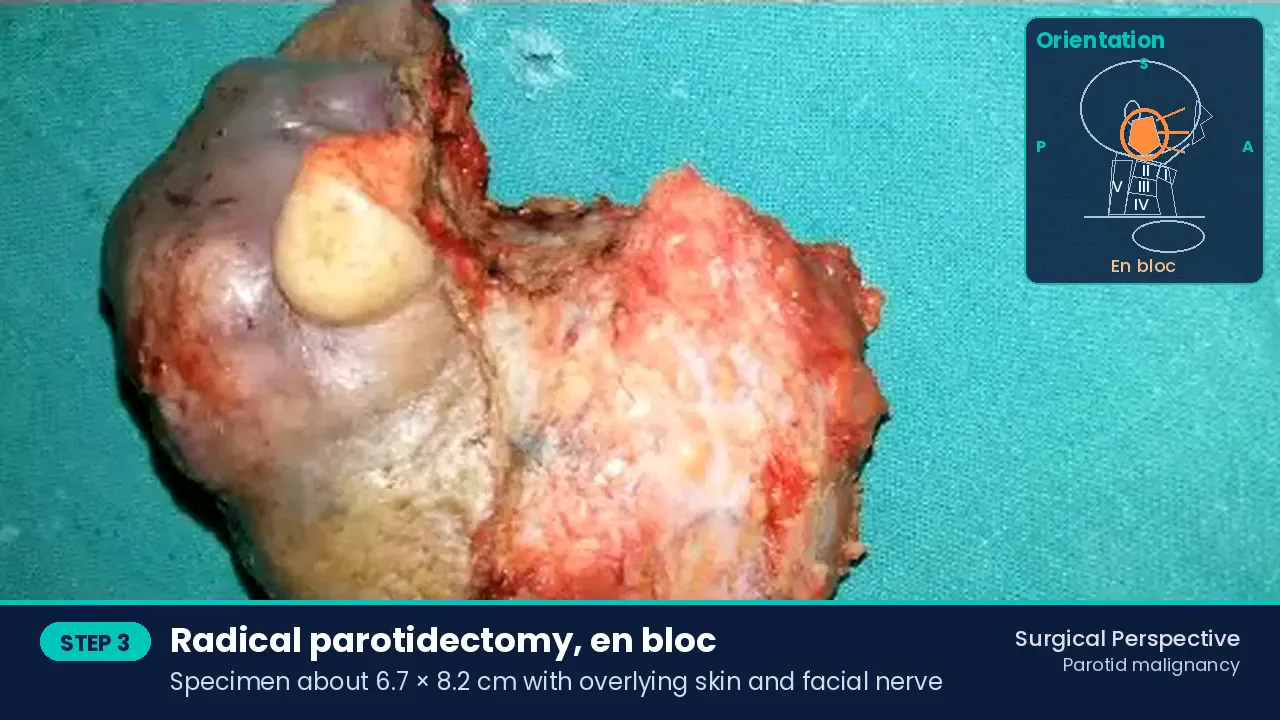
Parotid excised en bloc with the overlying skin and the infiltrated facial nerve; specimen about 6.7 × 8.2 cm.
Radical parotidectomy, en bloc Primary defect
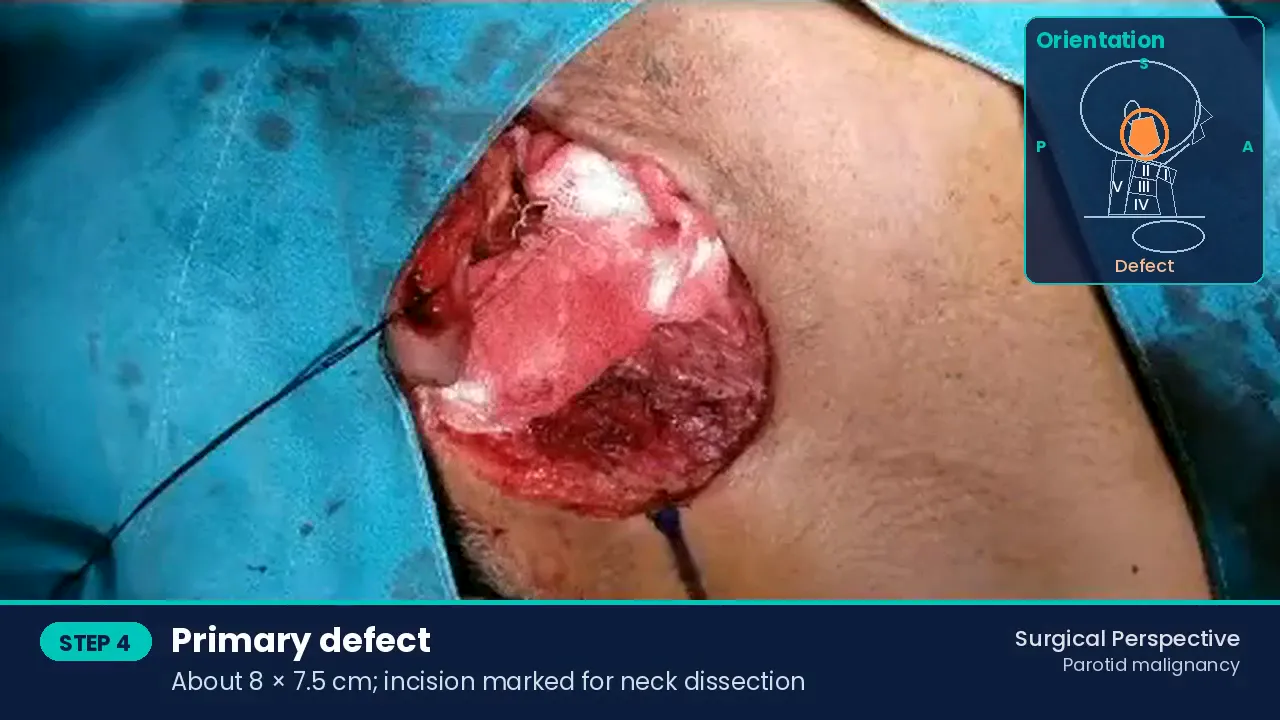
About 8 × 7.5 cm; incision marked for neck dissection.
Primary defect Radical neck dissection
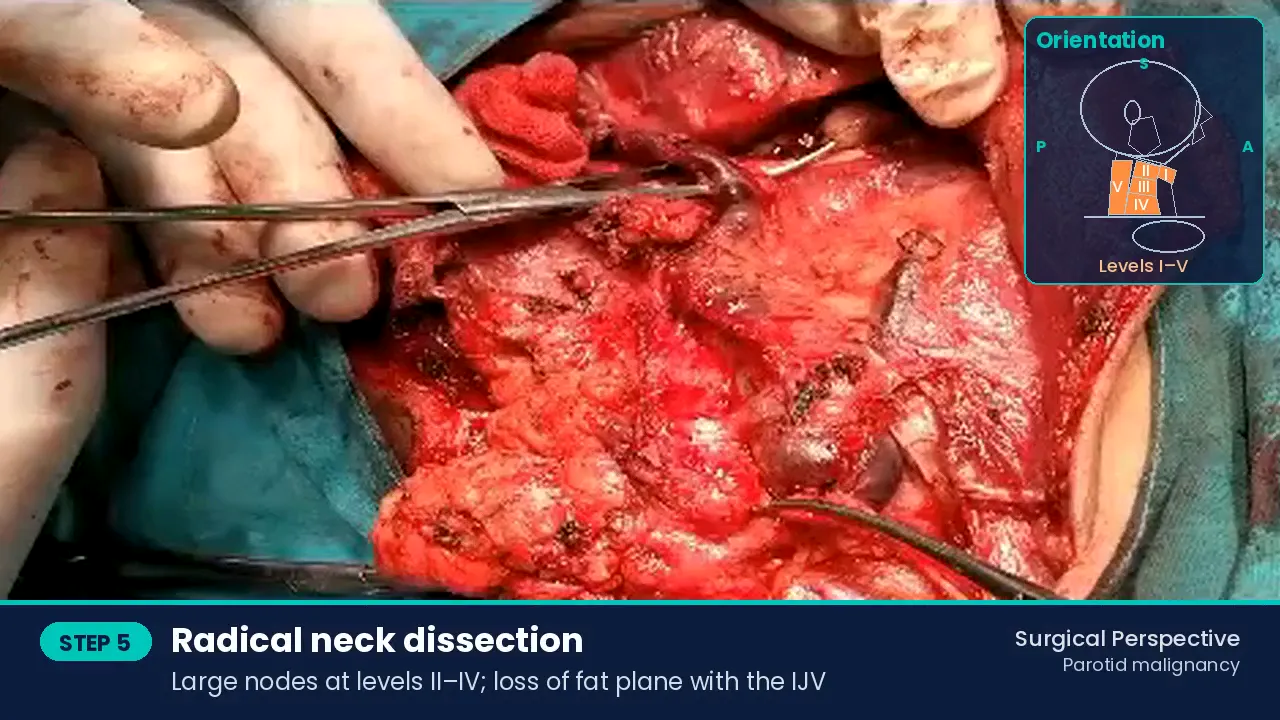
Levels I–V cleared with the sternocleidomastoid, internal jugular vein (large nodes at levels II–IV with loss of the fat plane around the IJV) and spinal accessory nerve.
Radical neck dissection Post-dissection anatomy
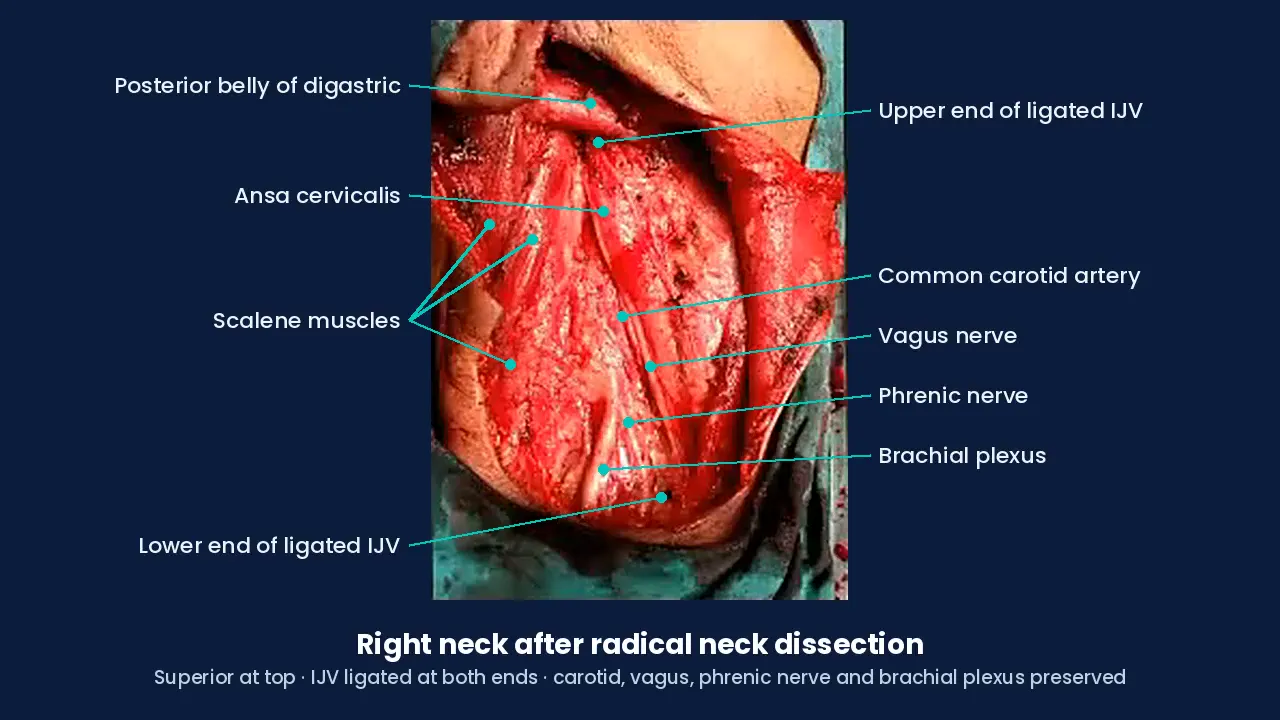
Structures preserved after radical neck dissection: common carotid artery, vagus and phrenic nerves, brachial plexus; IJV ligated at both ends; posterior belly of digastric, ansa cervicalis and scalene muscles identified.
Post-dissection anatomy Pectoralis major myocutaneous flap
Skin paddle marked over the pectoralis major; flap raised on the thoracoacromial vessels and tunnelled to the neck [2].
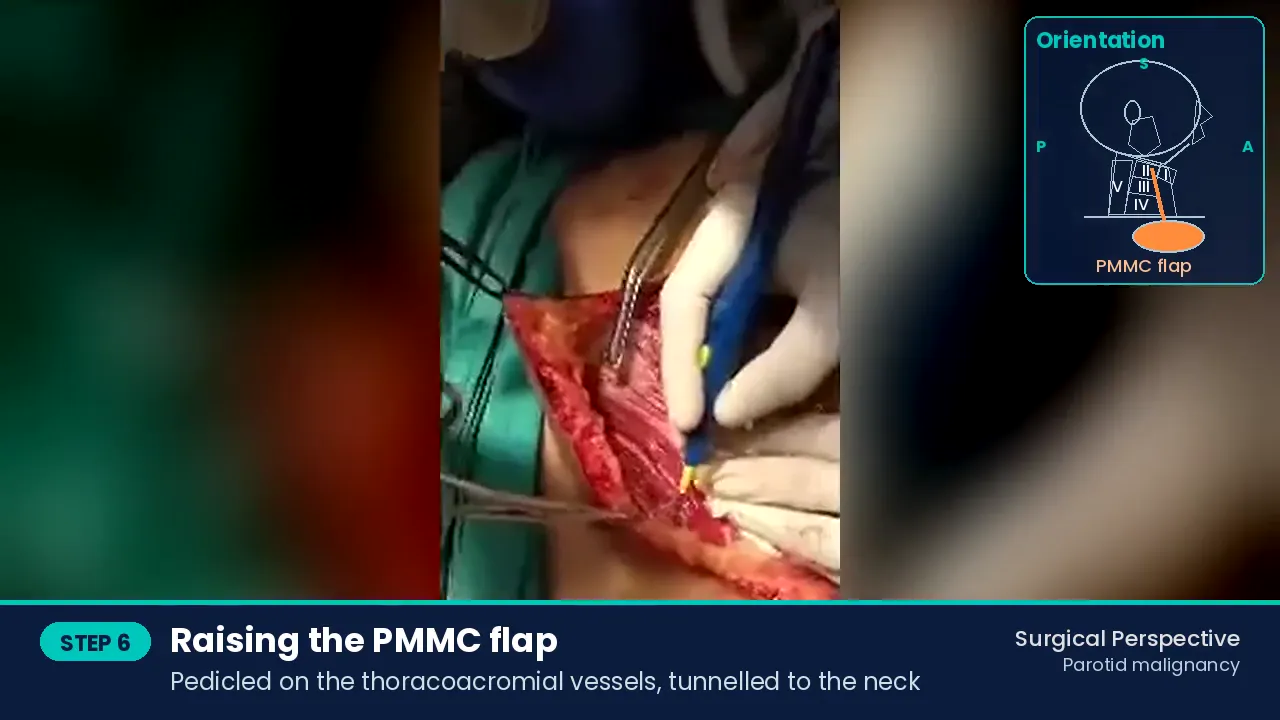
Pectoralis major myocutaneous flap Final result
Composite defect covered; neck and great vessels protected.
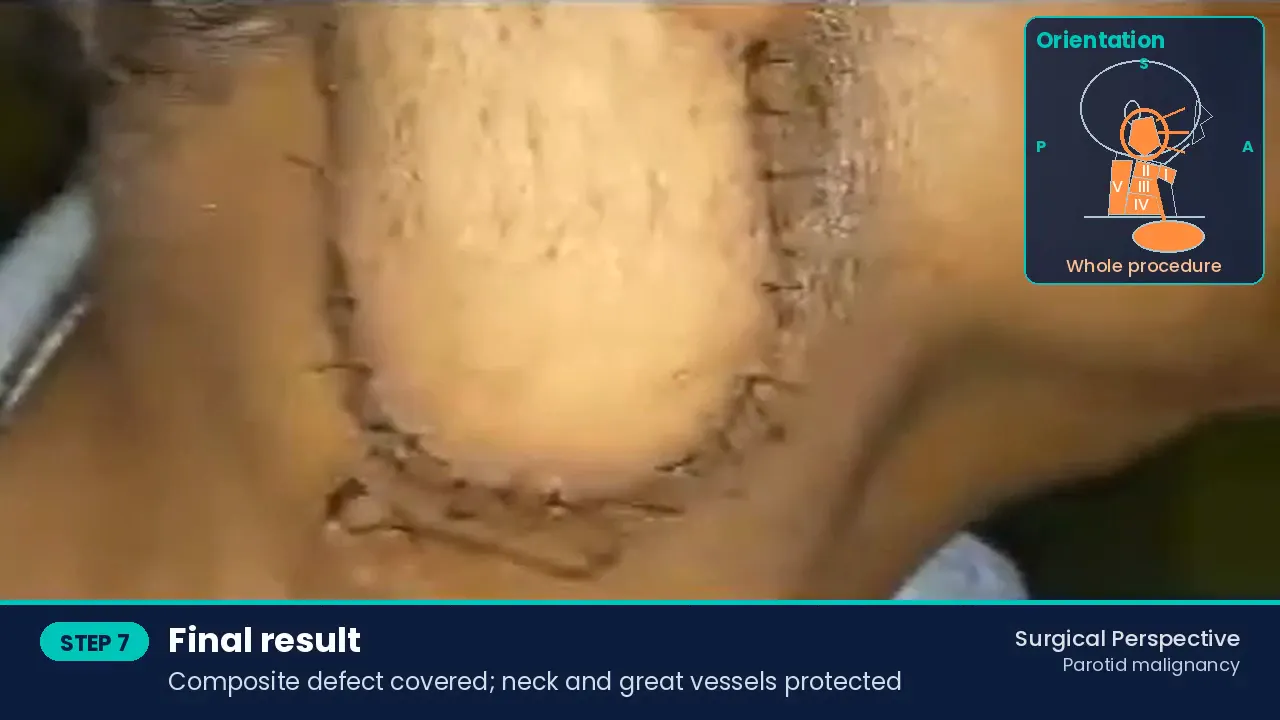
Final result
Postoperative management
- Adjuvant radiotherapy to the parotid bed and neck for high-grade, T4, node-positive disease [1].
- Flap monitoring; shoulder physiotherapy after accessory nerve sacrifice.
- Eye protection for the facial palsy; facial reanimation considered later where suitable.
Discussion
Facial nerve sacrifice is reserved for clinically or grossly involved nerves; pre-operative palsy indicates involvement. Skin infiltration requires en bloc excision with margin, and the composite defect over the great vessels needs well-vascularised cover. The PMMC flap remains a reliable workhorse for this purpose in a single stage.
Learning points
- A parotid mass with facial palsy is malignant until proven otherwise.
- Resect en bloc with skin and involved nerve; reconstruct in the same sitting.
- Node-positive high-grade disease: comprehensive neck dissection and adjuvant radiotherapy.
References
- Geiger JL, Ismaila N, Beadle B, et al. Management of salivary gland malignancy: ASCO guideline. J Clin Oncol. 2021;39(17):1909-1941. PMID 33900808. https://pubmed.ncbi.nlm.nih.gov/33900808/
- Ariyan S. The pectoralis major myocutaneous flap: a versatile flap for reconstruction in the head and neck. Plast Reconstr Surg. 1979;63(1):73-81.
Consent and ethics
Written informed consent was obtained for surgery and for de-identified use of clinical images and video for education. No identifying information is shown; eyes are blurred where visible. This report is for medical education and does not replace individual clinical advice.
Surgical team
Dr Bhushan Kathuria & Team, Santosh Advance ENT Healthcare, Hisar. Consultants: Dr Bhushan Kathuria, Dr Parmod Jangra, Dr Harshvardhan. Clinical fellows: Dr Ayush, Dr Iqrorjon. Team · Fellowship and previous fellows.
How to cite
Kathuria B, and Team. High-Grade Mucoepidermoid Carcinoma of the Parotid with Facial Nerve and Skin Involvement: Radical Parotidectomy, Radical Neck Dissection and PMMC Flap Reconstruction. Surgical Perspective · Surgical Case Reports. 2026. Available at: https://bhushankathuria.com/case-parotid-mucoepidermoid-carcinoma-radical-parotidectomy-pmmc.html
More case reports
Extended Total Maxillectomy with Infratemporal Fossa, Transpterygoid and Anterior Skull Base Clearance for Sinonasal Mucormycosis
Upfront radical resection for fulminant sinonasal mucormycosis
▶ Video + case report
Giant Pilomatricoma of the Neck Misdiagnosed as Tubercular Lymphadenitis: Wide Local Excision and Two-Stage Deltopectoral Flap Reconstruction
Pilomatricoma presenting as a non-healing neck mass
▶ Video + case report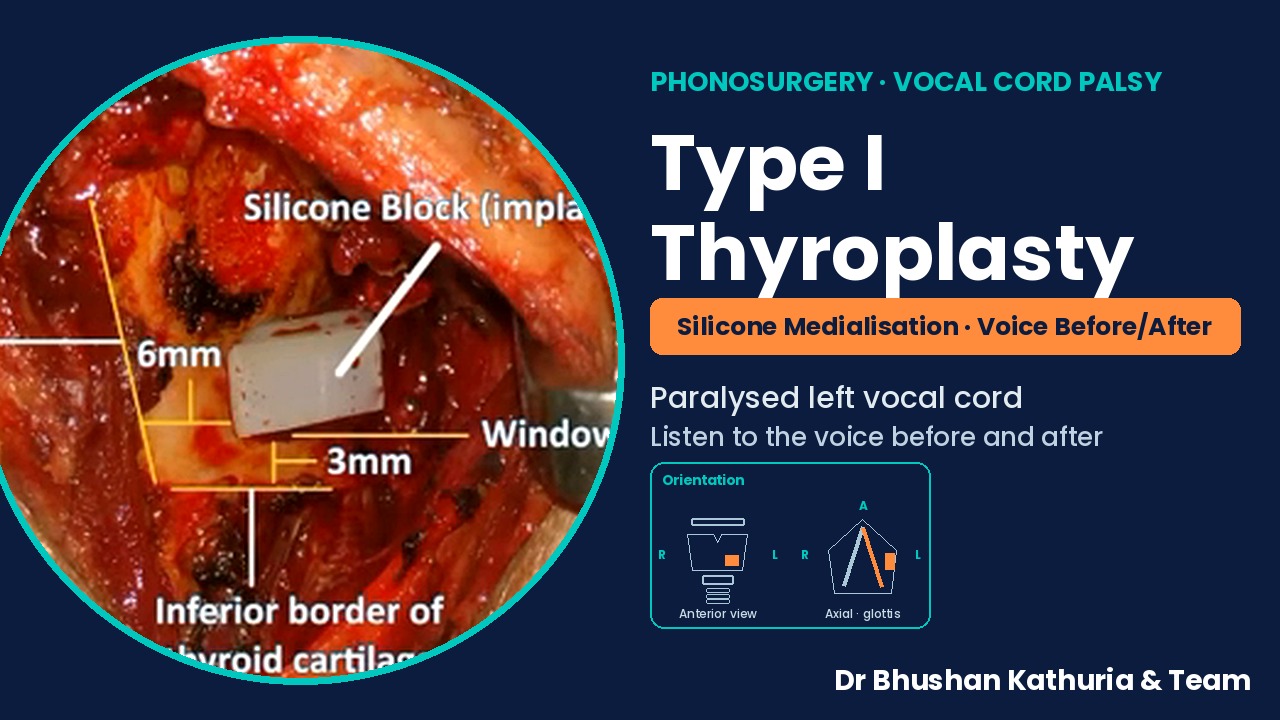
Type I Thyroplasty: Silicone Medialisation of a Paralysed Left Vocal Cord, with Pre- and Post-operative Voice
Medialisation thyroplasty for unilateral vocal fold palsy
▶ Video + case report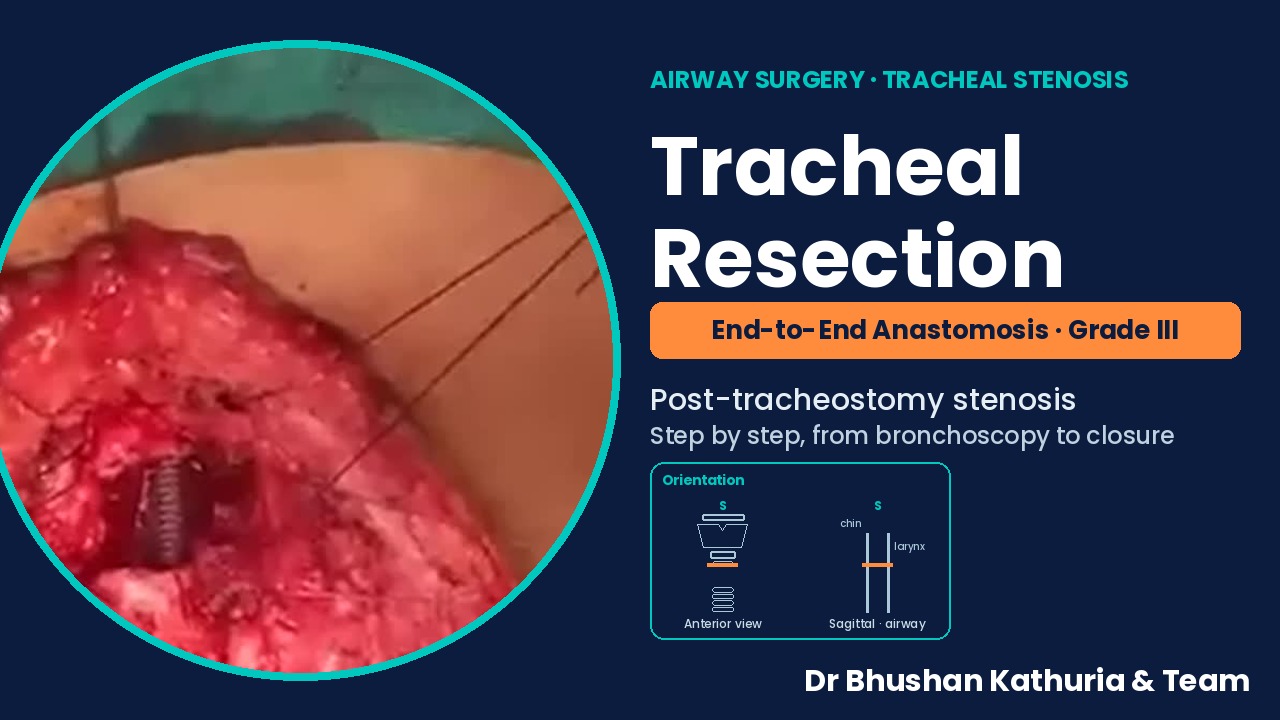
Segmental Tracheal Resection and End-to-End Anastomosis for Grade III Post-tracheostomy Tracheal Stenosis
Tracheal resection and primary anastomosis after failed decannulation
▶ Video + case report
Giant Goitre: Three Cases and Three Approaches — Cervical Delivery of Retrosternal Extension, Lateral Strap-Sparing and Midline Strap-Dividing Thyroidectomy
Three giant goitres, three surgical approaches
Case report
Glomus Jugulotympanicum, Two Cases from Pinna to Petrous: Facial Nerve Transposition with Carotid Control, and Facial Nerve Resection with Interposition Grafting
Two glomus jugulotympanicum cases: facial nerve transposition and facial nerve grafting
Case reportAll surgical case reports → · Head Neck Cancer · Throat Cancer · Videos · YouTube channel · WhatsApp channel