
Carcinoma of the Tonsillolingual Sulcus and Base of Tongue: Transoral Excision and Selective Neck Dissection through Two Transverse Incisions
Base of tongue carcinoma: transoral excision and selective neck dissection. Intended audience: ENT residents and head and neck surgeons.
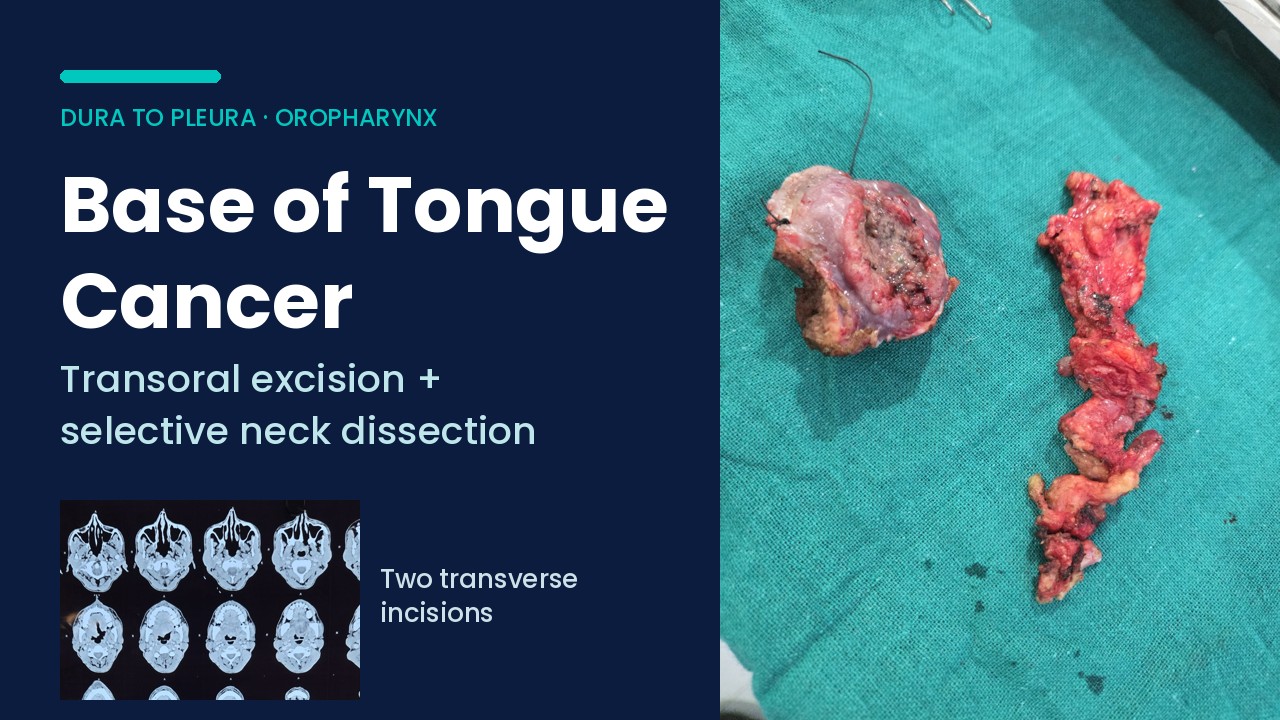
- Diagnosis
- Moderately differentiated squamous cell carcinoma, right tonsillolingual sulcus, base of tongue and vallecula, not crossing the midline
- Primary
- Transoral excision with a margin of healthy tissue; no mandibulotomy
- Neck
- Selective neck dissection through two parallel transverse incisions
- Video
- 2 min · 8 operative steps
Operative video with step captions and geometric orientation markings.
Abstract
An elderly man who smoked and drank alcohol presented with an ulcer in the throat and difficulty in swallowing. Endoscopy showed an ulceroproliferative lesion at the right tonsillolingual sulcus extending to the base of tongue and the vallecula, not crossing the midline; biopsy showed moderately differentiated squamous cell carcinoma. After a tracheostomy, the tumour was excised through the mouth with a margin of healthy tissue, without mandibulotomy, and a selective neck dissection was done in the same sitting through two parallel transverse incisions, with the specimen removed in one piece. The operative steps are shown, and the choice of a transoral approach for a lateralised tumour is discussed.
Keywords: base of tongue cancer; oropharyngeal carcinoma; tonsillolingual sulcus; vallecula; transoral excision; selective neck dissection; MacFee incision; tobacco and alcohol; p16
Introduction
Tobacco and alcohol together raise the risk of head and neck cancer more than either alone [1]. In such a patient a persistent throat ulcer or difficulty in swallowing should lead to early examination rather than repeated symptomatic treatment. Oropharyngeal carcinoma is staged and treated differently according to p16 (HPV) status, which carries independent prognostic value [2]. For small, accessible oropharyngeal tumours, transoral surgery with neck dissection and primary radiotherapy are both accepted options [3].
Case presentation
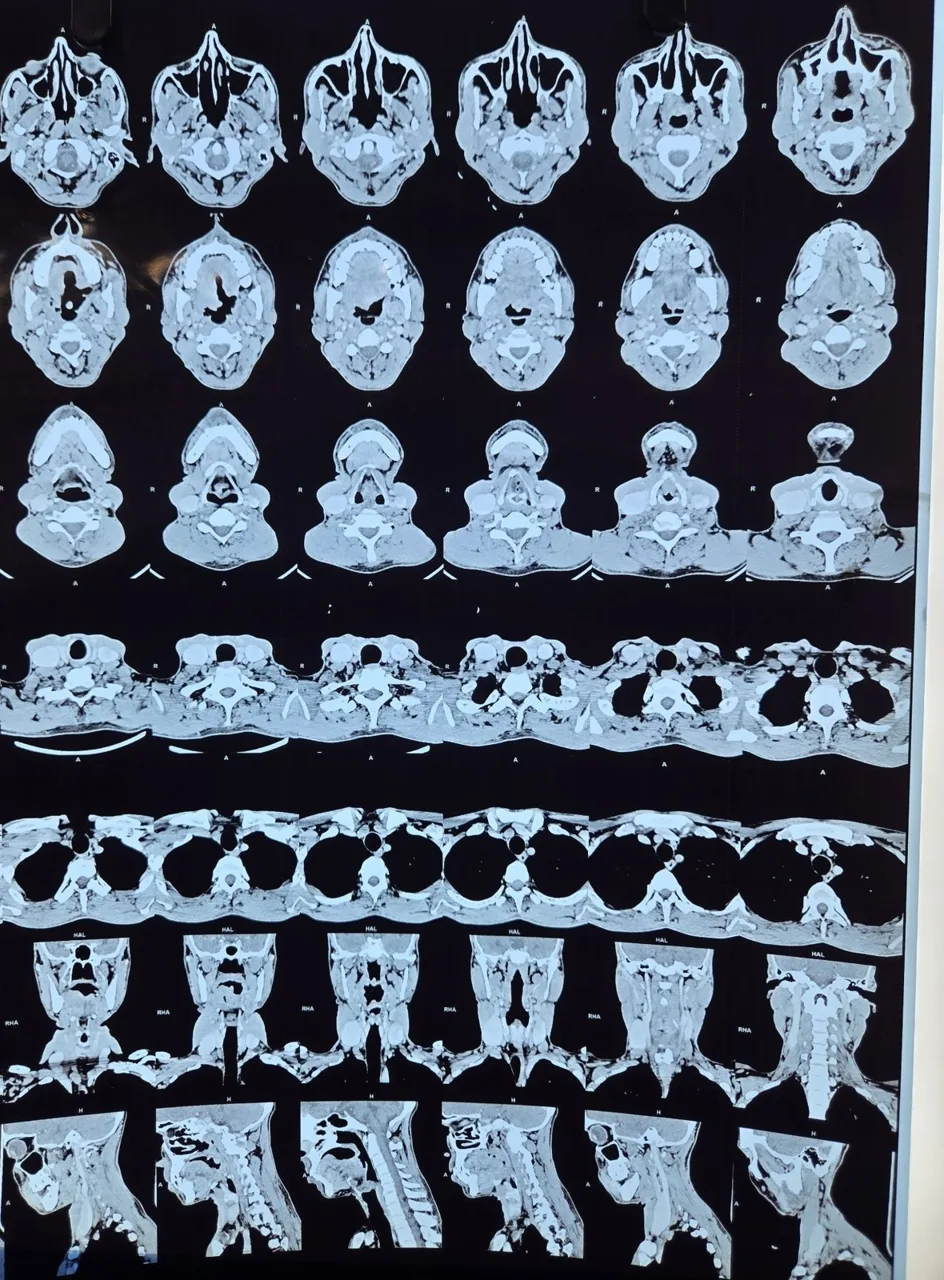
An elderly man who smoked and drank alcohol presented with an ulcer in the throat and difficulty in swallowing. Endoscopy showed an ulceroproliferative lesion at the right tonsillolingual sulcus extending to the base of tongue and the vallecula; it did not cross the midline. Biopsy showed moderately differentiated squamous cell carcinoma, and CT of the neck and upper chest was done for staging. Written informed consent for surgery and for de-identified educational use of images and video was obtained. Patient identity is not shown.
Surgical technique
Airway
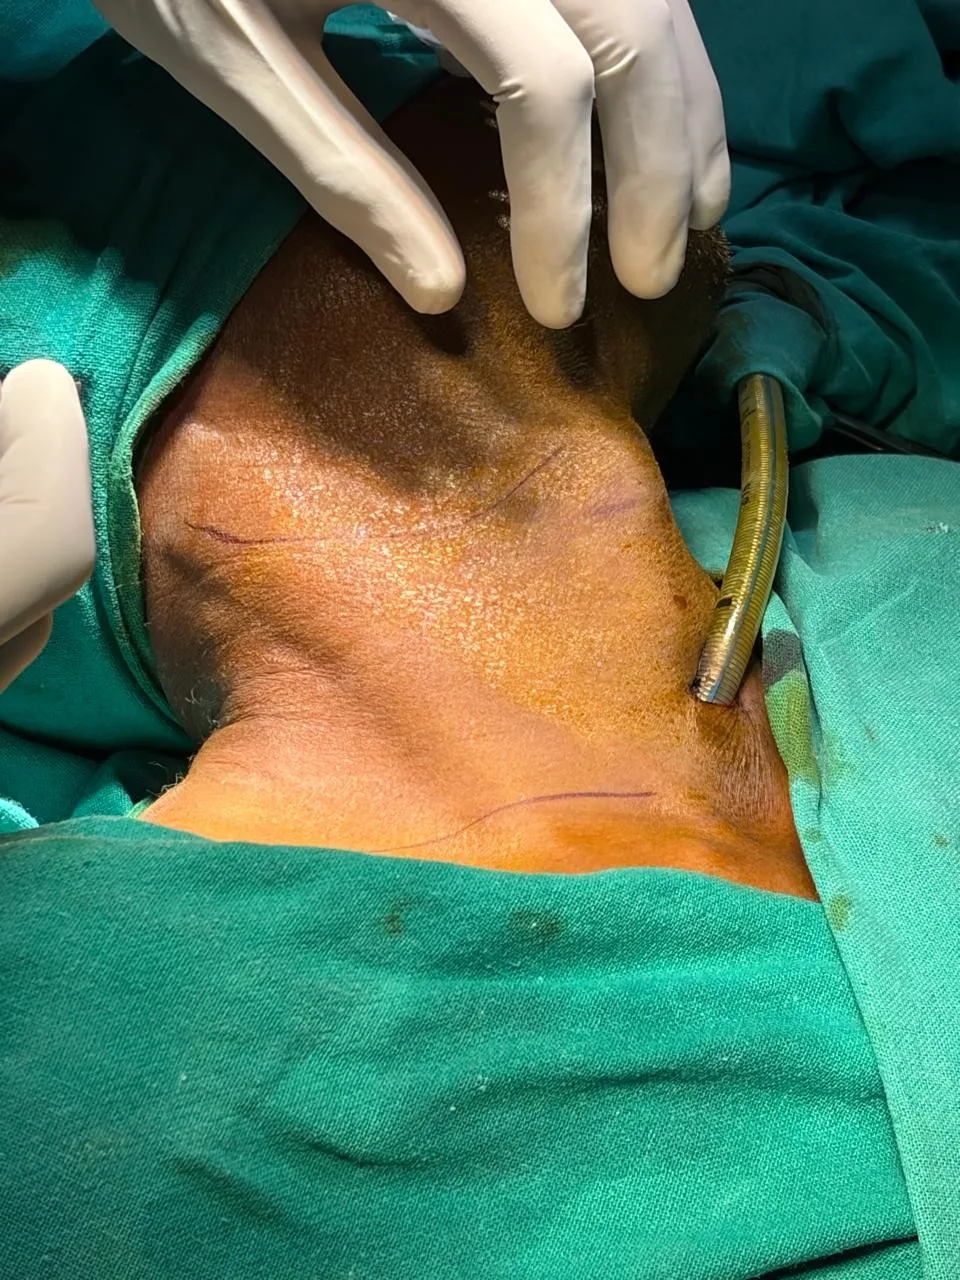
A tracheostomy secures the airway and keeps it away from the operative field; the two parallel transverse neck incisions are marked.
Airway Upper incision
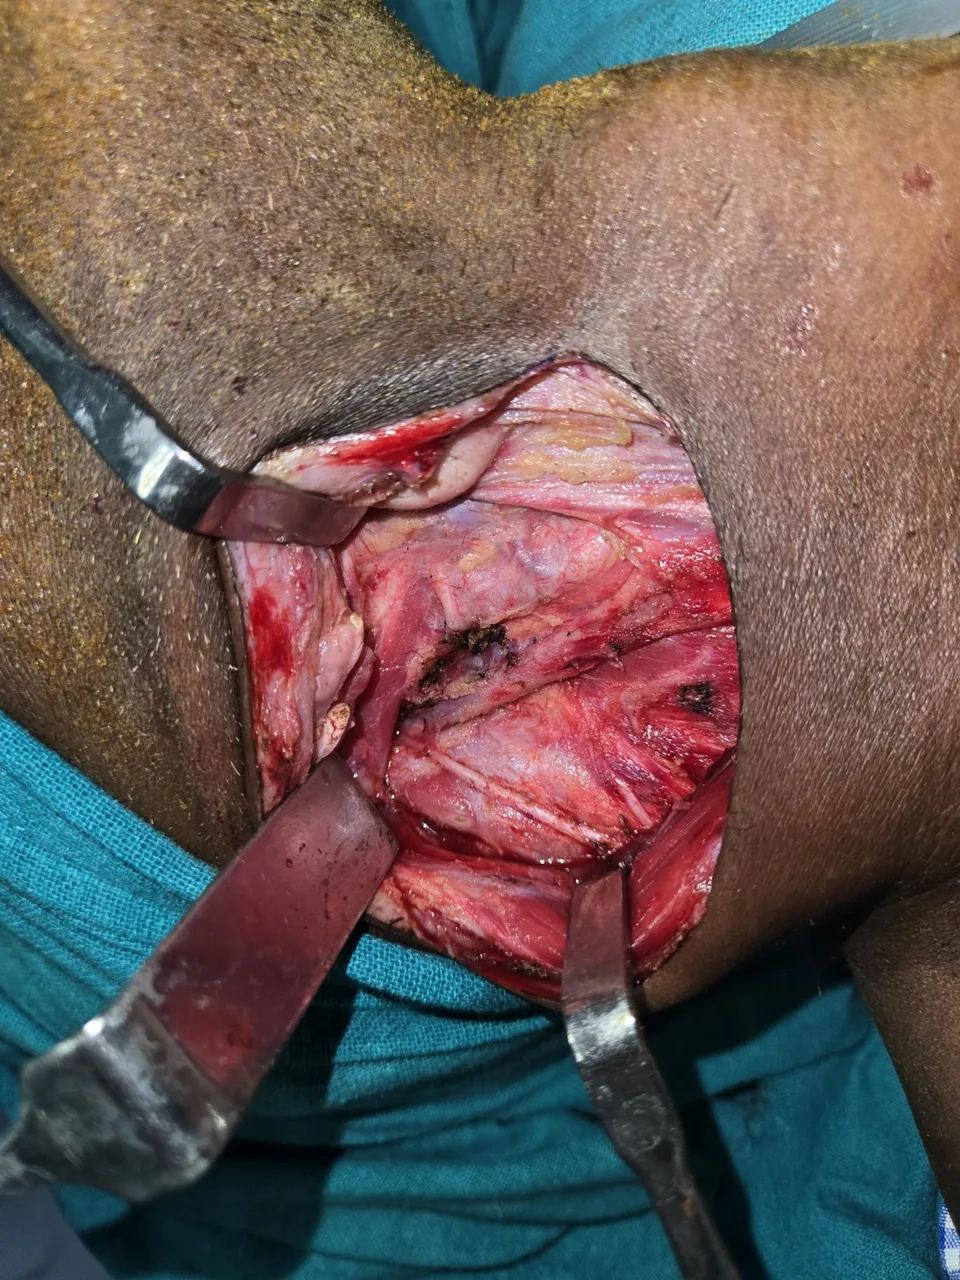
Subplatysmal flaps are raised through the upper transverse incision and the upper neck is exposed.
Upper incision Selective neck dissection
The selected nodal levels are cleared along the carotid sheath, working between the two incisions under the skin bridge [4].
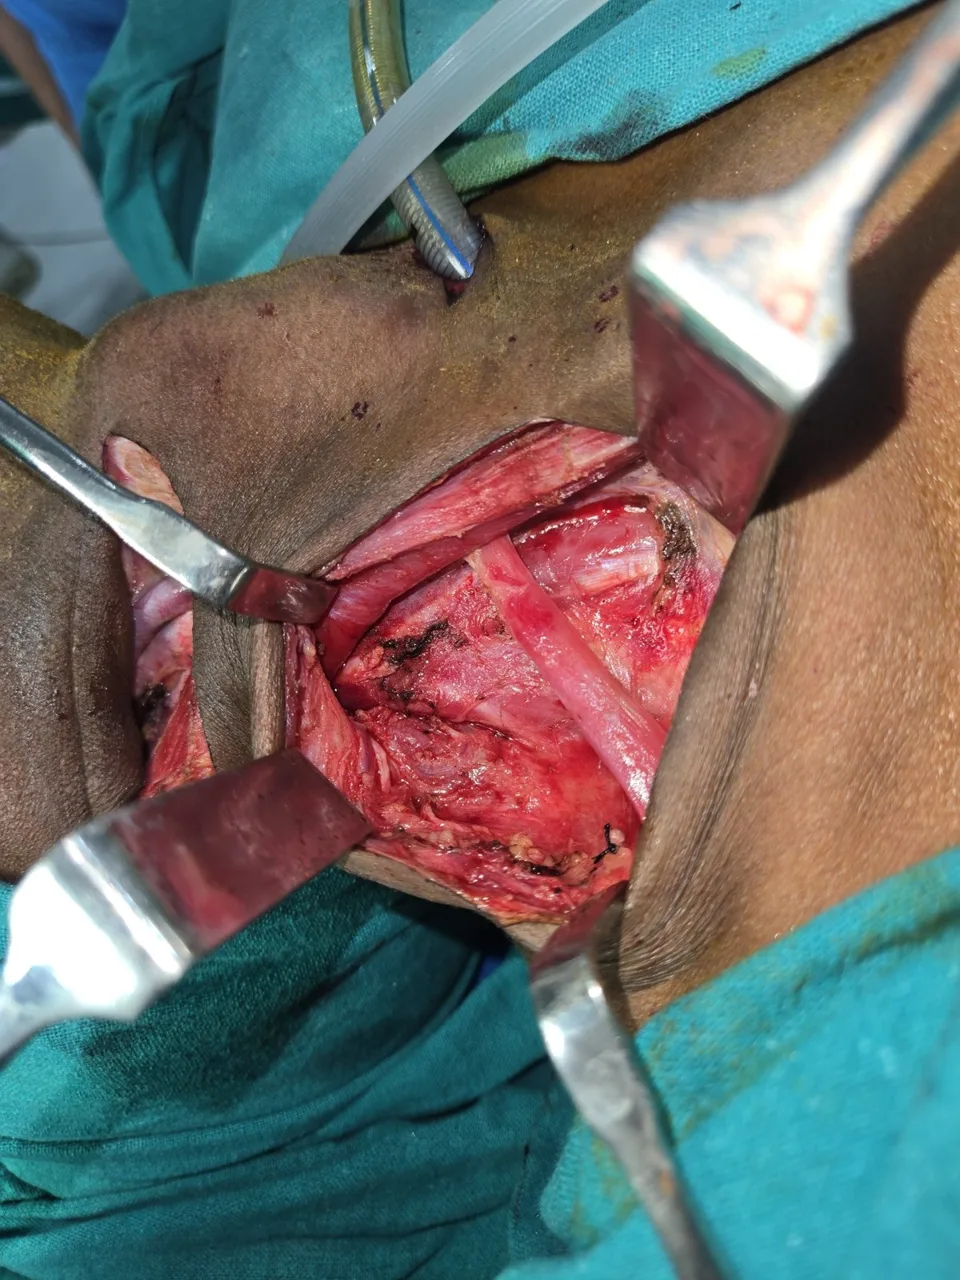
Selective neck dissection Both incisions
After the dissection both incisions are open and the skin bridge between them remains intact; the specimen is delivered in one piece.
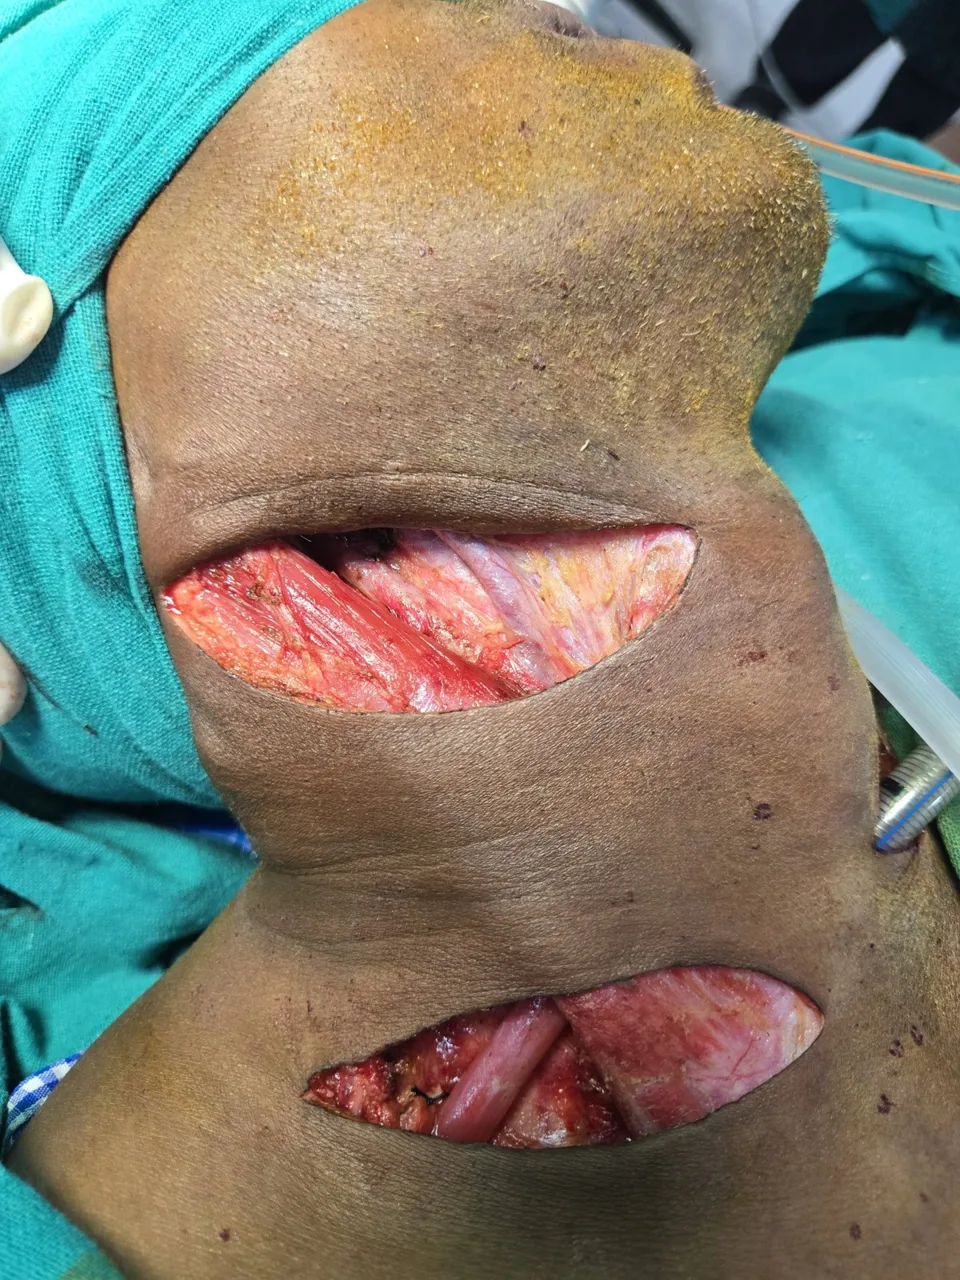
Both incisions Transoral excision
The tumour is exposed through the mouth and excised with a margin of healthy mucosa and muscle, without mandibulotomy, and marked with orientation sutures for the pathologist.
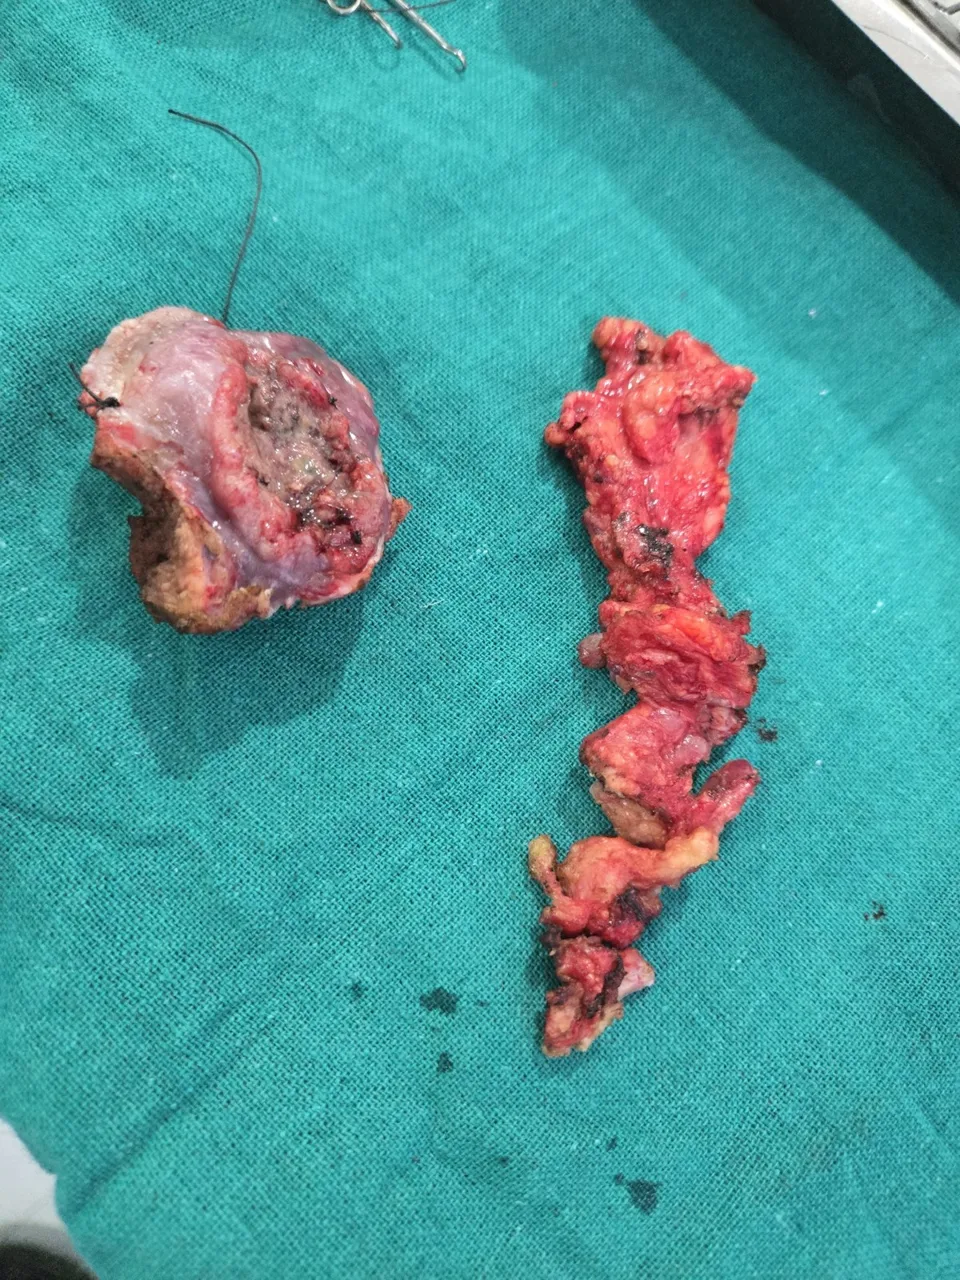
Transoral excision Primary specimen
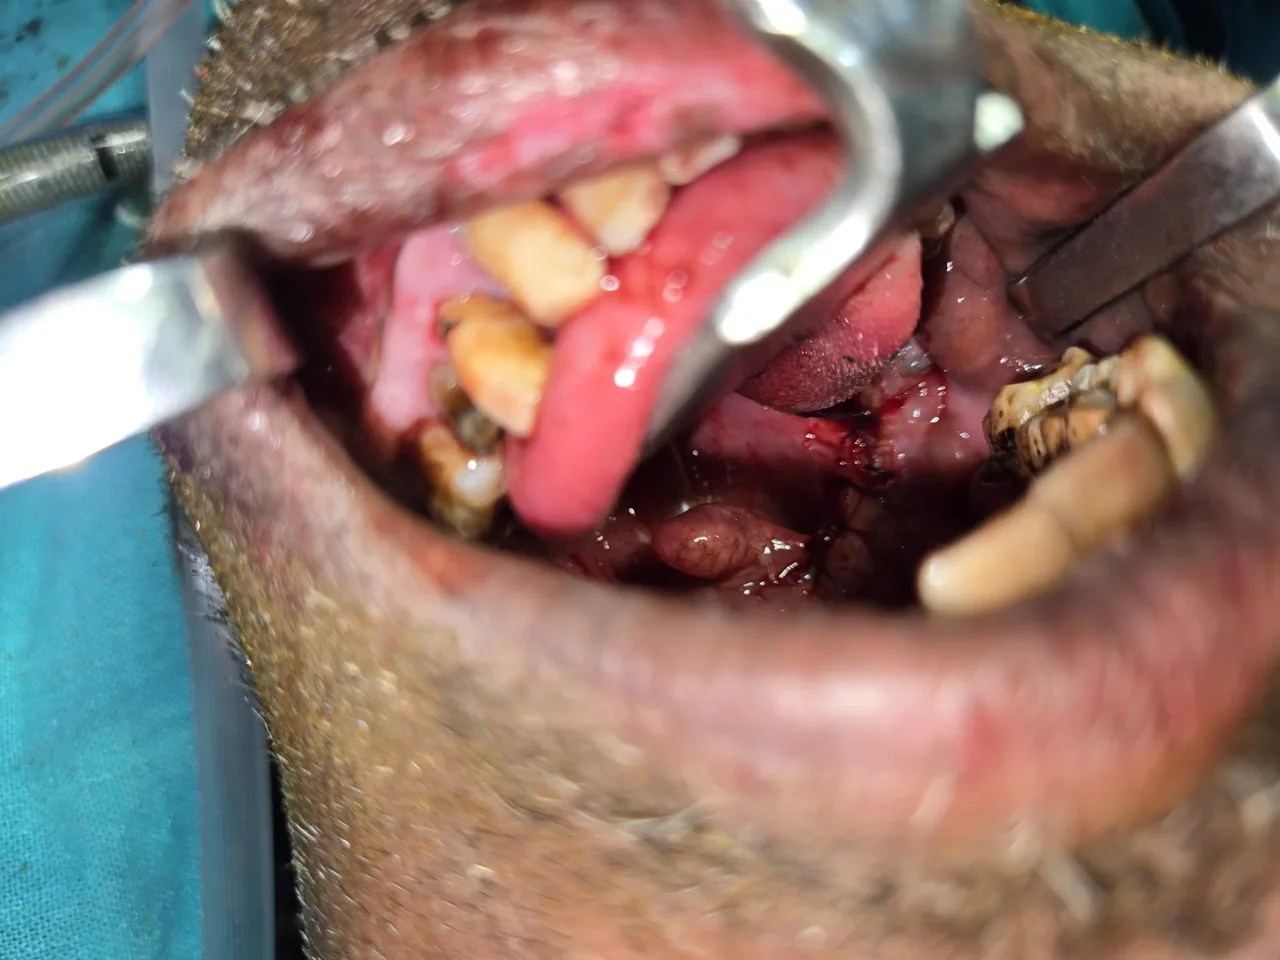
Ulceroproliferative tumour surrounded by a margin of normal mucosa.
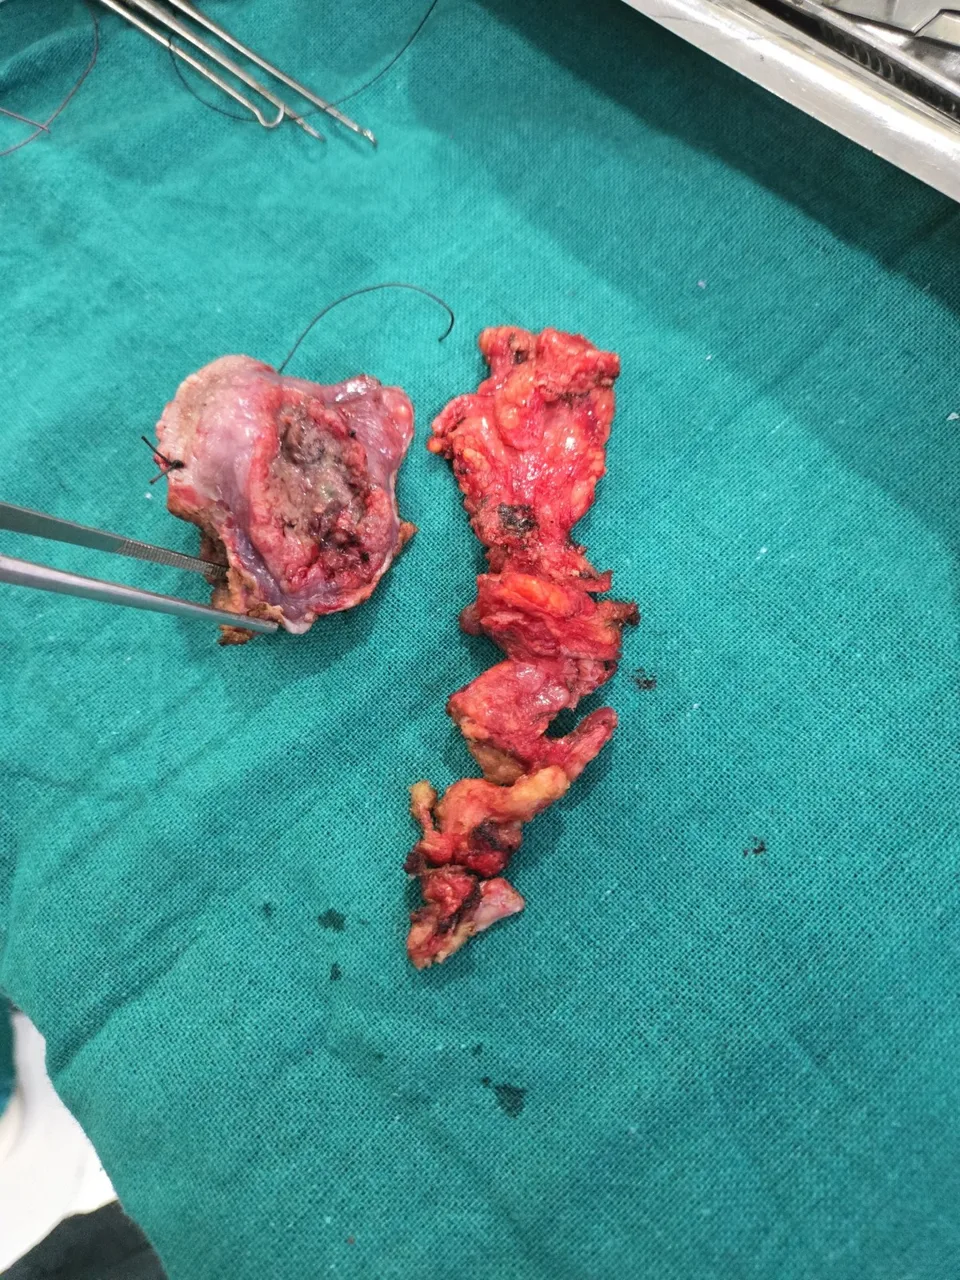
Primary specimen Closure
Haemostasis is secured and the excision site at the right tonsillolingual sulcus and base of tongue is sutured.
Closure
Postoperative management
- Tracheostomy care, with decannulation once the oropharyngeal swelling settles.
- Nasogastric feeding until swallowing is safe.
- Watch for early or secondary bleeding from the tonsillar and base of tongue bed, and for aspiration.
- Adjuvant radiotherapy or chemoradiotherapy decided on margins, nodal disease and extranodal extension.
- Advice to stop tobacco and alcohol; follow-up for recurrence and second primary tumours.
Discussion
A lateralised carcinoma of the tonsillolingual sulcus and base of tongue that does not cross the midline can be removed through the mouth with a margin of healthy tissue, avoiding a mandibulotomy, while the neck is treated in the same sitting. Two parallel transverse incisions, as described by MacFee, give access to the selected nodal levels while keeping well-vascularised skin flaps [4]. In a randomised comparison of transoral surgery with neck dissection against radiotherapy for early oropharyngeal carcinoma, swallowing-related quality of life at one year was slightly better after radiotherapy, though the difference did not reach the predefined clinically meaningful threshold; the choice rests on tumour access, the expected need for adjuvant treatment and the patient's preference [3]. p16 status should be recorded in every oropharyngeal carcinoma because it changes stage and prognosis [2].
Learning points
- A lateralised tumour that does not cross the midline can be excised through the mouth with a healthy margin.
- Treat the neck in the same sitting; two transverse incisions keep well-vascularised skin flaps.
- Test p16 in every oropharyngeal carcinoma.
- A throat ulcer, difficulty in swallowing or a neck lump for more than three weeks needs an ENT examination, especially in people who smoke or drink alcohol.
References
- Hashibe M, Brennan P, Chuang SC, et al. Interaction between tobacco and alcohol use and the risk of head and neck cancer: pooled analysis in the International Head and Neck Cancer Epidemiology Consortium. Cancer Epidemiol Biomarkers Prev. 2009;18(2):541-550. https://doi.org/10.1158/1055-9965.EPI-08-0347
- Ang KK, Harris J, Wheeler R, et al. Human papillomavirus and survival of patients with oropharyngeal cancer. N Engl J Med. 2010;363(1):24-35. https://doi.org/10.1056/NEJMoa0912217
- Nichols AC, Theurer J, Prisman E, et al. Radiotherapy versus transoral robotic surgery and neck dissection for oropharyngeal squamous cell carcinoma (ORATOR): an open-label, phase 2, randomised trial. Lancet Oncol. 2019;20(10):1349-1359. https://doi.org/10.1016/S1470-2045(19)30410-3
- MacFee WF. Transverse incisions for neck dissection. Ann Surg. 1960;151(2):279-284. https://doi.org/10.1097/00000658-196002000-00021
Consent and ethics
Written informed consent was obtained for surgery and for de-identified use of clinical images and video for education. No identifying information is shown; eyes are blurred where visible. This report is for medical education and does not replace individual clinical advice.
Surgical team
Dr Bhushan Kathuria & Team, Santosh Advance ENT Healthcare, Hisar. Consultants: Dr Bhushan Kathuria, Dr Parmod Jangra, Dr Harshvardhan. Clinical fellows: Dr Ayush, Dr Iqrorjon. Team · Fellowship and previous fellows.
How to cite
Kathuria B, and Team. Carcinoma of the Tonsillolingual Sulcus and Base of Tongue: Transoral Excision and Selective Neck Dissection through Two Transverse Incisions. Surgical Perspective · Surgical Case Reports. 2026. Available at: https://bhushankathuria.com/case-base-of-tongue-carcinoma-transoral-excision-neck-dissection.html
More case reports
Extended Total Maxillectomy with Infratemporal Fossa, Transpterygoid and Anterior Skull Base Clearance for Sinonasal Mucormycosis
Upfront radical resection for fulminant sinonasal mucormycosis
▶ Video + case report
High-Grade Mucoepidermoid Carcinoma of the Parotid with Facial Nerve and Skin Involvement: Radical Parotidectomy, Radical Neck Dissection and PMMC Flap Reconstruction
Composite parotid resection with single-stage PMMC reconstruction
▶ Video + case report
Giant Pilomatricoma of the Neck Misdiagnosed as Tubercular Lymphadenitis: Wide Local Excision and Two-Stage Deltopectoral Flap Reconstruction
Pilomatricoma presenting as a non-healing neck mass
▶ Video + case report
Type I Thyroplasty: Silicone Medialisation of a Paralysed Left Vocal Cord, with Pre- and Post-operative Voice
Medialisation thyroplasty for unilateral vocal fold palsy
▶ Video + case report
Segmental Tracheal Resection and End-to-End Anastomosis for Grade III Post-tracheostomy Tracheal Stenosis
Tracheal resection and primary anastomosis after failed decannulation
▶ Video + case report
Giant Goitre: Three Cases and Three Approaches — Cervical Delivery of Retrosternal Extension, Lateral Strap-Sparing and Midline Strap-Dividing Thyroidectomy
Three giant goitres, three surgical approaches
▶ Video + case report
Glomus Jugulotympanicum, Two Cases from Pinna to Petrous: Facial Nerve Transposition with Carotid Control, and Facial Nerve Resection with Interposition Grafting
Two glomus jugulotympanicum cases: facial nerve transposition and facial nerve grafting
▶ Video + case reportAll surgical case reports → · Head Neck Cancer · Voice Swallowing Breathing · Videos · YouTube channel · WhatsApp channel